Using the Airwareness App for Accessibility in Classrooms and Beyond
Table of Contents
Introduction
Air Support Project’s Airwareness Support App is a great visualization tool for comparing COVID-19 risks in your particular setting and situation at different airflow rates. In this blog we will show how to use the app to enhance airflow to mitigate risks of infection and reduce other indoor air contaminants. We will also show how the impacts of these air quality improvements in classroom settings can expand into the greater communities by preventing infections from turning into outbreaks, and outbreaks into surges.
By simulating enhanced airflow using the app, you can watch a space transform from virus-rich to virus-limited while an infectious person is present in the classroom. You can also determine the approximate time it takes to clear an environment from infectious doses after a person has left. By doing so in classrooms and other settings, you can create accessibility and inclusion for high-risk children, staff, and households with asthma, allergies, and chronic illnesses who are particularly susceptible to poor outcomes from inadequate indoor air quality.
Get monthly IAQ tips & simulation hacks—join our list here.
Enhanced airflow also improves the efficiency of masks in preventing infections. Creating a setting where one-way masks are more effective is a significant step toward creating inclusive, safe spaces reducing overall transmission risks to occupants.
What Does Indoor Air Quality Have to Do with Accessibility?
Turns out, a lot! Many children and staff in schools have health conditions, like asthma and allergies, that require better air quality than the status quo to avoid worsening of conditions. Nearly 28 million people (1 in 12) in the U.S. have asthma. It is a leading chronic disease in children, affecting 4.9 million. Among children ages 5 to 17, asthma is one of the top causes of missed school days, accounting for more than 13.8 million absences in 2013 (AAFA, Asthma Facts). Environmental allergies are also extremely common, affecting approximately 81 million people in the U.S, or 26% (67 million) of adults and 19% (14 million) of children in 2021 (AAFA, Allergy Facts).
Children are largely exposed to allergy and asthma triggers in their schools. Researchers have discovered an epidemic of asthma attacks and hospitalizations occurring in the month of September, shortly after kids start school, due to their increased exposure to triggers common in classrooms; including viruses (responsible for 80% of asthma attacks in children), mold, pollen, pet allergens, wildfire smoke, and more.
And these things can affect more than just the kids in the classroom. Allergens like pet hair can be carried between classrooms and homes on children’s clothes and belongings, where it can affect allergic children and other family members with asthma or allergies by getting into their homes (AAFA, September Asthma Epidemic).
Similarly, viruses can also be transferred back and forth between classrooms and home environments. A 2023 study showed that more than 70% of US household COVID spread started with a child. The resulting illness of a child’s family members, including young siblings and adult caretakers with higher risk conditions, can have significant effects on the health, finances, and wellbeing of households. Furthermore, surges in the general population closely follow when kids return to school after breaks.
CDC data over the past five years indicates that COVID surges are common each year after children return to school in the fall, as well as when children return to school after winter break. Increases in travel and indoor gatherings during breaks increase infection risks, and these infections are then brought into schools where they can be amplified into outbreaks.
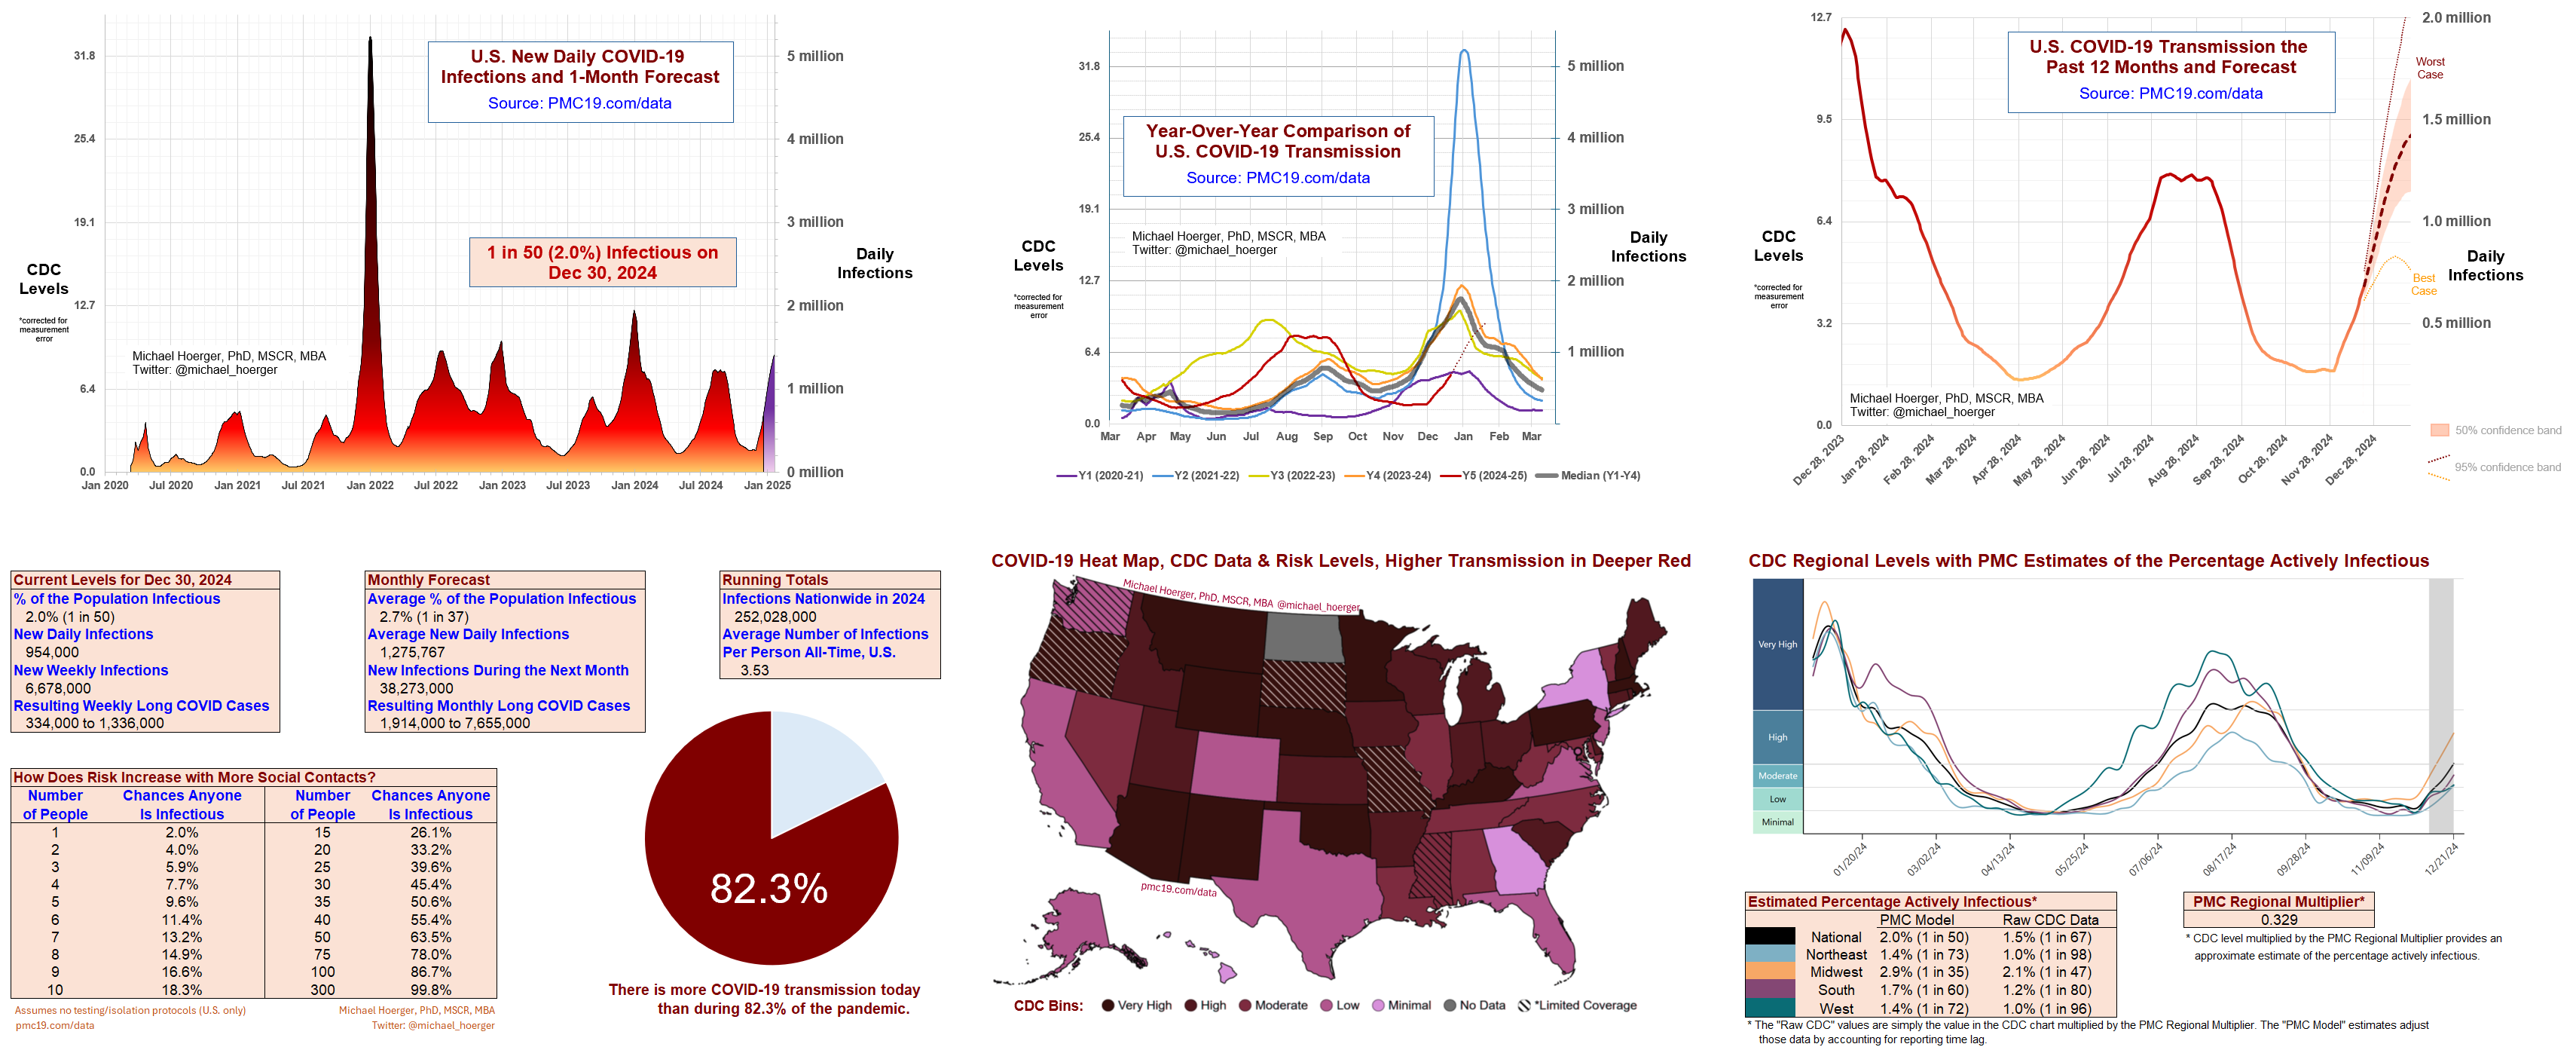
According to wastewater analysis, on December 30th 2024 there was a nearly a 40% chance that at least one person in a room of 25 was actively infectious. This means in most classroom settings, there is a high likelihood that at least one student is infectious with COVID-19, and transmission risks in normally ventilated classrooms are very high (as we will see by using the Airwareness app later in this blog).
Large numbers of students in one room, attendance policies that encourage presenteeism, few people masking, and the lack of enhanced airflow in classrooms can create recipes for infectious disease outbreaks. These infections not only cause absences for students, but they can result in long-term health impacts (long COVID) for people of all ages and health statuses, including serious impacts on the brain, IQ, and cognition. See Mounting Research Shows That COVID-19 Leaves Its Mark on the Brain, Including Significant Drops in IQ Scores, The Conversation. Other research shows that vaccination does not reduce these risks, with one researcher stating:
“Because vaccination prior to infection does not decrease the neurological manifestations of long COVID, it is critical to keep our communities safe from both acute COVID-19 infection and potential long-term neurological manifestations.”
Dr. Koralnik
The health burden is exceptionally high amongst those children, staff, and households with common chronic health conditions – who have an even higher risk of health complications from both the initial infection, as well as in the long-term. These families may already avoid higher-risk activities like traveling and attending large gatherings, but they often cannot–nor should they have to–avoid in-person education. In-person education should not be a higher risk activity, but as we can see from exposure risks to infectious viruses, and the impacts of other indoor air irritants, contaminants, and allergens common in classrooms, it is a higher risk environment for many people. In the November 2024 Safer shared air – a critical accessibility and inclusion issue report by the Safer Air Project, founder Plum Stone stated:
“It’s time to recognise that people living with high-risk conditions need safe access to public spaces without risking their health due to airborne infections, and to make indoor air safe for everyone to breathe. To do so, we need to set and implement indoor air quality performance standards that effectively lower the risk of infection from airborne pathogens, and the health impacts of other pollutants, to achieve accessible public spaces for everyone.”
Plum Stone
So what exactly are these air quality performance standards, and how can we measure and achieve them? This is where Air Support Project’s new Airwarenss Support App steps in.
Airwareness Support App for Risk Assessment
Air Support Project recently created an Airwareness Support App—a free, browser-based tool that simulates indoor air quality scenarios and helps you assess and reduce airborne infection risks by customizing room size, airflow (ventilation and filtration), occupancy, and pathogens to make smarter, healthier indoor decisions. You can learn more at our Blog Introducing the Airwareness Support App, and use it yourself here.
What is great about the Airwareness app is that you can see what normally would be invisible– each red dot in the room representing an infectious dose of COVID-19. As the app runs over time, these infectious doses increase based on the custom inputs for your simulation.
Note: You can make the time speed up faster by adjusting the speed multiplier which will appear by hovering your mouse over the time function (circled in red). Move the speed back down once you are at the time you want to observe, and look at the Transmission Tile to view the infection risk.
COVID-19 is by far the most difficult-to-control indoor air quality issue due to its rapid evolution, year-round prevalence, high contagiousness, and ability to linger in the indoor air while remaining infectious over long periods of time (see Defining the Problem). Yet, as you will see by using the app, these risks can be mitigated. In doing so, the levels of other indoor contaminants, ranging from wildfire smoke to allergens, can also be reduced in indoor spaces.
See real-time app tips & success stories—follow us on X, Instagram & LinkedIn.
Average Classroom Simulation: Transmission Risks at Different Air Changes Per Hour
In the freeze images from our Average Classroom Simulation using the Airwareness App below, you can easily see the difference between a classroom with 1 air change per hour (ACH) – which is common in many classrooms around the country – and at 6 and 12 air changes (ACH) -which are commonly recommended as standards for control of infectious aerosols in classrooms. In this app simulation, we used settings for an average sized classroom of 23 occupants, with 1 of them being actively infectious, and ran it for 2 hours for each airflow we tested. Here are the results in Image 5.
You may ask why all the infectious doses (red dots) are not cleared even after 12 ACH? It is because, when one infectious person is present in the classroom, they will be continuously exhaling infectious aerosol for as long as they remain present (and even after they leave, it will take time to clear out–or purge– the lingering virus). Over time, even with a high ACH, a small amount of infectious doses will accumulate in the air. Transmission risks increase the longer the infectious person and the exposed people are in the same space, based on the amount that accumulates (which will be much higher with poor airflow than with enhanced airflow). For this reason, it is recommended to wear a mask in shared indoor spaces with other households. And, as we will see in the next section, masks are much more able to prevent infections in spaces with enhanced airflow, which is why the two make such a great pair when it comes to preventing infections!
The amount of airflow, often measured as air changes per hour (ACH), will determine how many infectious doses (red dots) build up over time (also known as the viral density). The viral density matters for both masked and unmasked occupants in the classroom, both while the infectious person is present and after they leave. Let’s look into why.
Why does viral density matter?
You may recall from our previous blog: “The Interplay of Time, Viral Density, and Filtration”, that exposure duration (how long you are in a space with infectious doses for) and the concentration of viral particles in the air can influence the effectiveness of infection prevention measures.
In particular, we highlighted a 2021 study that examined the role of viral density on the ability of a person to prevent themselves from being infected by wearing a mask one-way (when they, as the uninfected, are in a room with an infected person). It was here that researchers found that there is a vital difference in the effectiveness of masks in “virus-rich” versus “virus limited” environments.
As you can see in Image 8, a person masked in a virus-limited space can avoid an infection they would have gotten unmasked. However, in a virus-rich setting, they are at risk of infection even when masked. The researchers state:
1- That masking achieves large reductions in infection probability when the maskless infection probability is low (such as setting with fewer infectious doses in the air). However, there is a steep decrease in the masks efficacy in the virus-rich regime (when there are more infectious doses in the air). In all regimes, N95 masks are more protective than surgical masks, but all masks are impacted significantly by viral density.
2- That viral aerosols (<5 μm) contain more viruses than the droplets (>5 μm) and that viral aerosols can enhance their transmission because smaller particles remain suspended for a longer time, which leads to stronger accumulation and dispersion in the air. This may cause higher airborne virus concentrations, inhaled virus numbers, and infection risks, especially in densely occupied rooms with poor ventilation and long periods of exposure.
3- That ventilation and purification can change an environment from a virus-rich to a virus-limited condition, which may be particularly important for places with relatively high SARS-CoV-2 (the name of the virus that caused COVID-19) abundances.
In order to maintain safety, accessibility, and inclusion, classrooms need to be virus-limited settings. This will enable staff, students, and households–especially those with higher risk conditions– to be able to protect their health with masks that are not as effective without enhanced airflow. It will also reduce transmission risks for other unmasked occupants. By adding the correct amount of portable HEPA purifiers and/or MERV-13 fan-and-filter air cleaners, one can reduce infections by approximately 65-90% (the higher end of this range being achieved by combining enhanced airflow with masking).
Using the Airwareness App, we can more easily see how enhanced airflow can transform a virus-rich setting into a virus-limited setting, and reduce the chances of infection.
Average Classroom Simulation: Comparing Purge Time at 1 ACH and 6 ACH
Enhanced airflow will also reduce the amount of time it takes for infectious aerosols to be purged after the infectious person leaves the classroom. The Airwareness App can be used to determine the approximate purging time needed, using its Vacate Rooms Function.
For this simulation, we used the same classroom setting parameters as above with one infectious person being in the classroom for 2.0 hours at 6 ACH. We then clicked the person running button (next to the time function). It turns yellow once clicked, and it indicates the infectious person vacating the space.
We continued to run the app, watching as the 6 ACH cleared out the red dots (infectious doses). At 2.4 hours (24 minutes after the infectious person left), all the infectious aerosols were removed. This is significantly faster than what would have occurred at 1 ACH, which our simulation shows took 6 hours to clear out all infectious aerosols!
Reducing the viral density, and the amount of time spent in higher densities, significantly reduces transmission risks, while also increasing the efficacy of masks.
Conclusion
Clean, healthy indoor air isn’t a luxury—it’s a fundamental part of making schools and other public spaces truly accessible to everyone. By reducing airborne contaminants and managing ventilation effectively, we empower individuals who are most at risk—those with asthma, allergies, and chronic health conditions—to fully participate in daily life without fear of serious health repercussions. From classroom attendance to overall community wellbeing, the benefits of improved air quality ripple far beyond the school walls, helping prevent outbreaks, surges, and long-term health complications.
Just as ramps and elevators are recognized as tools for physical accessibility, better ventilation and air filtration must be understood as tools for respiratory accessibility. With the Airwareness Support App, we can visualize how small changes in airflow translate to life-changing improvements for students, staff, and families. Let’s seize the opportunity to transform our buildings into safer, more inclusive spaces—because every child and every adult deserves the right to breathe easy and thrive.
Now that you know some of the things our Airwareness Support App can do, check out our Guide on How to Use the Airwareness Support App to create your own customized simulations.
Fuel clean-air solutions—make your tax-deductible gift today here.
"Children are the world's most valuable resource and its best hope for the future."
John F. Kennedy
SHEA O'NEIL
Volunteer
Creator of COVID-conscious advocacy works: writings, art, and social networking. BA degree in psychology, with over 11 years of continued education studies in allergy and autoimmune research, and continued research the past 3 years into airborne irritants and COVID-19. Parent, disabled rights advocate.
Sarah Masih, MD, MBA
Sarah Masih is the Executive Director of Air Support Project and has extensive experience in project management, fundraising, and communications. Her deep commitment to public health and her collaborative approach with community organizations and health experts make her a vital force in the fight for cleaner air and healthier communities.
Melissa Smallwood
Melissa Smallwood is Science and Technology Policy researcher with a background in neuroscience, psychology, and social science, and the author of The Future of Long COVID: A Threatcasting Approach. They are interested in how disability and healthcare justice intersect with emerging technologies, and are an advocate for COVID mitigation strategies to help end the pandemic.
Epi-Yeti
Fueling a revolution for cleaner air, I'm the creative powerhouse behind the Air Support Project's groundbreaking open-source technology. With a fiery passion and a rich background in non-profits, I'm on a mission to clear the skies and transform lives worldwide.
This content is published under a creative commons — attribution/no derivatives license.
KNOW BETTER, BREATHE BETTER.
“I must fight with all my strength so that the little positive things that my health allows me to do might be pointed toward helping the revolution. The only real reason for living.”
FRIDA KAHLO